


Types of Acne Scars, Boxcar, Rolling & Icepick scars
Acne vulgaris is the most prevalent skin condition in the United States, and the American Academy of Dermatology reports that up to 50 million Americans are affected each year. Researchers estimate that one in five individuals with acne breakouts will develop an acne scar. Acne scars arise when the skin’s natural healing response produces an inappropriate amount of new collagen, either too much or too little, to repair damage caused by inflammatory acne lesions. Treating acne scars can often be even more difficult than addressing the initial breakouts and, for many, may lead to feelings of self-consciousness or low self-esteem. Consulting an experienced, board-certified dermatologist like Dr. Michele Green in NYC is the best way to create a safe, effective acne scar treatment plan.
Acne scars fall into two main classifications: atrophic and hypertrophic. Atrophic scars, including rolling, boxcar, and ice-pick types, are depressions in the skin’s surface that form when too little collagen is produced. Hypertrophic scars, including keloids, are raised scars that form when too much new collagen is produced. Although not classified as true acne scars, dark spots called post-inflammatory hyperpigmentation can also develop after inflammatory acne. No two individuals develop scars in the same way, and most patients with acne scars have a mix of several types, requiring a tailored treatment approach to reduce their appearance effectively. Non-invasive treatment options include traditional and radiofrequency microneedling, subcision with dermal fillers, laser resurfacing, steroid injections, and chemical peels, depending on the type of acne scars you have. When you consult with Dr. Green, she will assess your unique combination of acne scars and customize a treatment plan that leaves you with smooth, beautiful skin that lasts.
What is an acne scar?
Acne scars develop when inflammation associated with an acne lesion causes irreparable damage to the underlying skin tissue. The skin then undergoes a natural wound-healing process that stimulates collagen production and helps repair the damage. Collagen is a protein essential for providing the skin with structure, firmness, and suppleness. Acne scars develop when collagen production is insufficient or excessive. Atrophic or depressed scars form when too little new collagen is produced, while hypertrophic or raised scars form when too much collagen is produced. Dark spots left behind on the skin from acne lesions are called post-inflammatory hyperpigmentation (PIH). PIH is not an actual acne scar; it occurs when the skin cells that produce pigmentation (skin color) are overactive during the healing process.

What are the different types of acne scars?
There are two main categories of acne scars: atrophic and hypertrophic. Atrophic acne scars are the most common type. They develop when the skin’s natural wound-healing response produces insufficient new collagen, resulting in depressions or indentations in the skin. Depressions in the skin’s surface characterize these scars. The three types of atrophic scars are rolling, boxcar, and ice-pick. Hypertrophic scars are thick, firm, raised scars that occur when the skin’s natural wound-healing response produces too much new collagen. They commonly develop in response to deeper wounds. Hypertrophic scars typically affect areas of the body such as the chest, back, shoulders, and jawline. Acne scars can also vary in severity, ranging from mild to moderate to severe. While not classified as an actual acne scar, post-inflammatory hyperpigmentation is often lumped together with acne scars, as these dark marks can be left behind after inflammatory acne lesions.
Rolling scars
Rolling scars are the shallowest type of atrophic scars, appearing wavy, uneven, and rough on the skin’s surface. They lack sharply defined borders and instead have sloping edges. These scars get their name from bands of scar tissue and fibrous tethers that develop between the skin’s surface and the underlying subcutaneous tissue. The fibrous bands pull down on the epidermis, creating the rolling, wavy appearance. Rolling scars are typically several millimeters wide and most commonly affect areas of the face, such as the jawline and cheeks.
Rolling scars most commonly develop from inflammatory acne, particularly moderate-to-severe cystic or nodular acne that damages the deeper layers of the skin. When acne lesions penetrate the dermis, the wound-healing process can produce fibrous bands rather than smooth, even collagen, anchoring the skin’s surface to the underlying tissue. As these bands mature and contract over time, they pull the epidermis downward at various points, creating the sloping, wavy texture characteristic of rolling scars. The longer active acne goes untreated, the more pronounced this scarring tends to become. Rolling scars can also result from chickenpox, other skin infections, surgical incisions, or traumatic injuries that disrupt the skin’s normal healing process.
Boxcar scars
Boxcar scars are atrophic scars with a round or oval shape, well-defined edges, and deep vertical sides. These scars often resemble chickenpox scars and are usually wider than other atrophic scars. Boxcar scars range from superficial to deep, depending on the extent of skin atrophy resulting from previously inflamed and infected acne lesions.
Boxcar scars typically develop after inflammatory acne, particularly cystic or nodular breakouts, that cause significant tissue damage and destroy collagen during healing. As inflammation damages the deeper layers of the skin, the body cannot fully rebuild the lost collagen and tissue, leaving a depressed area with sharply defined edges rather than a smooth, tapered indentation. Because this tissue loss tends to be broad and uniform across the affected area, boxcar scars often appear wider and more rounded than icepick or rolling scars. Other causes include traumatic injuries, insect bites, and surgical scars, particularly when the wound becomes infected or heals poorly.
Ice-pick scars
Ice-pick scars are atrophic scars with deep, narrow, V-shaped indentations on the skin’s surface. They are typically 2 mm or less wide and often resemble enlarged pores. This type of acne scar appears as though the skin were punctured with a sharp instrument, such as an ice pick. Ice-pick scars extend deep into the skin’s dermal layers and are often caused by severe inflammation associated with nodular or cystic acne lesions. Due to their deep, narrow nature, ice-pick scars are considered the most challenging acne scars to treat.
Ice-pick scars typically form after deep, inflamed acne lesions, such as cysts or nodules, cause significant damage to the skin’s structure. As these lesions penetrate the dermis, they destroy collagen and underlying tissue along a narrow path, and the skin heals by collapsing inward rather than regenerating lost volume. This narrow, deep pattern of tissue destruction gives ice-pick scars their characteristic V-shaped, puncture-like appearance. Because the damage extends so deep into the skin, these scars are especially difficult to treat with resurfacing methods alone. Ice-pick scars can also result from chickenpox lesions that become deeply inflamed, as well as from infected insect bites or other skin infections that penetrate the dermis.
Hypertrophic scars
Normal hypertrophic scars appear as raised, growth-like lumps of scar tissue. They do not extend beyond the original wound and may regress on their own. Normal hypertrophic scars can produce approximately three times the amount of new collagen typically produced during wound healing, forming new collagen fibers that develop in a uniform pattern and raise the lump.
Hypertrophic scars typically form after deep or significant injuries that damage both the epidermis and dermis, triggering an overactive wound-healing response. During healing, the body produces excess collagen at the wound site. When this collagen forms faster than it can be broken down and remodeled, it accumulates, forming a raised, thickened scar. Common causes include acne lesions, surgical incisions, burns, piercings, vaccinations, and other skin trauma, particularly when the wound is under tension, stretched, or experiences prolonged inflammation during healing. Individuals with darker skin tones and those with a family history of raised scarring are more likely to develop hypertrophic scars. Unlike keloids, hypertrophic scars remain confined to the boundaries of the original wound and may gradually flatten and fade over time.
Keloid scars
Keloid scars are a type of hypertrophic raised scar that usually grows larger than the initial wound. These scars may continue to grow after the wound has fully healed and will not regress on their own. Keloid scars can produce up to 20 times as much new collagen, and the collagen fibers form in a random arrangement. Keloid scars are particularly challenging to treat because removing them can stimulate new collagen production, leading to recurrence. Some individuals are more prone to developing keloid scars than others due to a genetic predisposition. Additionally, patients with darker skin tones are typically more susceptible to developing keloids than those with lighter skin tones. Treatment for keloid scars includes intralesional cortisone injections, silicone gel and sheets, and VBeam laser for associated pigmentation.
Keloid scars typically develop after any injury that damages the skin, including acne lesions, surgical incisions, burns, piercings, vaccinations, insect bites, or even minor cuts and scratches. In genetically predisposed individuals, the wound-healing process becomes dysregulated, causing fibroblasts to continue producing collagen long after the wound is repaired. Rather than stopping once the injury has healed, collagen production persists, causing the scar to extend beyond the original wound’s borders and continue to grow over time. Because the underlying tendency toward excess collagen production remains active even after the keloid is removed, new trauma to the area, including surgical excision itself, can trigger the same overactive response and cause the keloid to recur, often larger than before.
What causes the different types of acne scars?
Acne scars (sometimes written online as acne-scars) form when inflammation from a breakout damages surrounding tissue and disrupts the skin’s normal collagen production. Superficial breakouts, such as blackheads, rarely leave lasting marks because the inflammation never reaches the deeper layers of skin. However, severe acne that presents as pustules, nodules, or cysts penetrates much deeper into the dermis, triggering an exaggerated wound-healing response. When too little collagen is produced during this process, the result is atrophic scarring, while an overproduction of collagen leads to raised, hypertrophic scars. Left untreated, these breakouts can lead to permanent scarring, which is why Dr. Michele Green recommends treating active cystic acne as early as possible to help prevent it.

What are the best acne scar treatment options?
Many safe and effective noninvasive treatments for acne scars are available, including resurfacing lasers, subcision, chemical peels, and microneedling. Physicians often combine these because scar types vary. Internationally renowned, board-certified dermatologist Dr. Michele Green customizes each patient’s treatment plan with the most appropriate cosmetic procedures and specially formulated skincare products to achieve a smooth, healthy complexion.
Subcision with Dermal Fillers
Subcision is a minimally invasive procedure for treating atrophic acne scars, mainly rolling and boxcar scars. Dr. Green uses a sterile needle to break apart the scar tissue tethering the skin’s surface to its underlying layers, then injects dermal fillers into the depressions to restore volume that subcision alone cannot achieve. Dr. Green often uses Juvederm and Restylane, hyaluronic acid fillers that last 6 to 12 months. In contrast, Sculptra, made of poly-L-lactic acid, stimulates collagen production and can last up to two years.
Fraxel Laser Treatment
The Fraxel Dual laser is a non-ablative procedure that improves acne scars, fine lines, uneven texture, and pigmentation. Dr. Green calls it the “magic eraser” for its versatility. It uses fractional laser technology to create controlled microscopic wounds that stimulate new collagen production, with little to no downtime because only a fraction of the skin is treated at a time. Patients typically need three to five sessions spaced one month apart.
eMatrix Sublative Resurfacing Laser
The eMatrix laser reduces acne scars, fine lines, enlarged pores, and stretch marks by using bipolar radiofrequency energy to stimulate collagen production in the dermis while leaving the epidermis untouched. Downtime is minimal, with only mild redness that resolves within 48 hours, and it’s safe across all skin types and tones. Typically, four to six sessions are needed, spaced one month apart.
VBeam Pulsed Dye Laser Treatment
VBeam is the gold-standard treatment for redness, including acne-related inflammation, using targeted light to destroy red pigment while sparing the surrounding skin. It’s especially effective for post-inflammatory hyperpigmentation and red acne scars, with zero downtime and built-in cooling technology for comfort. Patients typically need four to six sessions.
Trichloroacetic Acid (TCA) Chemical Peels
TCA peels exfoliate the skin to reveal a smoother, brighter surface while stimulating new collagen. They’re effective for acne scars, hyperpigmentation, and acne, though they’re better suited to fair to light skin tones because darker skin is more prone to pigmentation. Multiple sessions are typically required.
TCA Cross
In this technique, a high concentration of TCA is applied directly to an atrophic scar, producing a “frost” that encourages peeling over several days. It’s best suited for medium-to-deep ice-pick scars and requires strict sun protection afterward. Only a board-certified dermatologist should perform this procedure to avoid pigmentation changes or scarring.
Mesopeels for hyperpigmented scars
Mesopeels are specialized peels containing lightening agents such as tranexamic acid, kojic acid, and azelaic acid to gently exfoliate and reduce melanin production. No downtime is required, and they’re safe for all skin tones, including darker skin. Multiple sessions are needed for best results.
Microneedling Collagen Induction Therapy
Microneedling uses ultra-fine needles to create controlled micro-injuries that stimulate the production of new collagen and elastin, improving skin texture, reducing fine lines, minimizing enlarged pores, and reducing pigmentation. It also increases absorption of topical serums, which is why Dr. Green often adds PRP, derived from the patient’s own blood, to enhance results. Patients typically need three or more sessions.
Vivace Radiofrequency Microneedling
Vivace combines radiofrequency technology with microneedling to improve acne scars, skin tone, elasticity, and texture. This combination maximizes collagen production across multiple skin layers without downtime, making it safe and effective for all skin tones, including sensitive and darker skin. Three or more sessions are typically recommended.
Microdermabrasion for Acne Scars
Microdermabrasion gently removes the top layer of dead skin cells using a microcrystal spray or a diamond-tipped handpiece, stimulating collagen production and improving tone and texture. It’s best for mild atrophic scars, and multiple treatments are needed for optimal results.
Dermabrasion for Acne Scars
Dermabrasion is a more aggressive version of microdermabrasion that removes superficial skin layers with a high-speed rotating wheel and typically requires anesthesia and about two weeks of downtime. Results are more dramatic, but the risk of infection, permanent discoloration, or scarring is higher.
Cortisone Injections for Hypertrophic Acne Scars
Intralesional cortisone injections effectively flatten raised scars and keloids while shrinking active acne lesions. A series of injections is typically needed, with 50 to 80 percent of keloid scars responding well. Dr. Green prefers this over cryotherapy because it carries a lower risk of side effects.
Punch Excision for Deep Ice-Pick Scars
Punch excision removes a small portion of the scar with a punch biopsy tool, and the wound is sutured or closed with adhesive. Punch grafting uses a skin graft from the back of the ear to cover deeper defects. This procedure is reserved for deep, extensive scars and should only be performed by a board-certified professional.
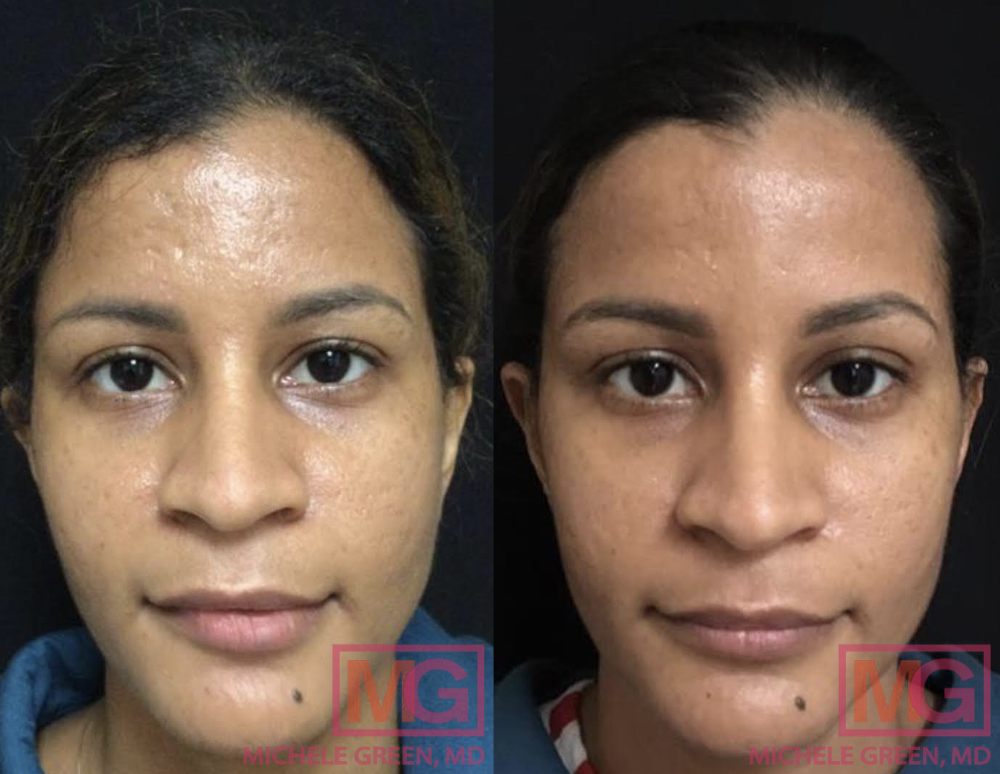
Frequently Asked Questions (FAQs) About the Different Types of Acne Scars
What is Post-inflammatory hyperpigmentation?
Post-inflammatory hyperpigmentation (PIH) is not considered true acne scarring because it does not cause irreversible damage to the underlying skin tissue or impair collagen production. PIH refers to the dark spots that may remain after an acne lesion or other inflammatory skin condition (such as a wound or a rash) heals. The color of the dark spots associated with PIH varies and can appear as brown, black, red, pink, or purple patches, depending on the patient’s skin tone. During the skin’s natural healing process, skin cells involved in healing the area may also overproduce melanin, leading to areas of concentrated hyperpigmentation. Although this type of hyperpigmentation may fade on its own, it can take a long time to fade fully without cosmetic intervention.
What are the 7 types of acne?
Acne can present in several forms, and knowing your type can help predict your risk of scarring. The seven main types of acne include blackheads and whiteheads (non-inflammatory acne), along with the inflammatory forms: papules, pustules, nodules, cysts, and acne conglobata, a rare and especially severe form of cystic acne. Non-inflammatory acne breakouts are less likely to cause scarring, while inflammatory acne breakouts—especially nodules and cysts—carry the highest risk of permanent scarring. If you experience frequent acne breakouts of any kind, seeing a board-certified dermatologist like Dr. Green early can help reduce your risk of developing acne scars.
What kind of acne scars won’t go away?
Unfortunately, most acne scars are permanent and will not disappear without intervention. While dark spots associated with post-inflammatory hyperpigmentation may fade over time, atrophic and hypertrophic scars are usually permanent. Acne scars frequently cause self-consciousness and low self-esteem, and their presence can be a painful reminder of past breakouts. However, the appearance of acne scars can be significantly improved. Expert board-certified dermatologist Dr. Michele Green has over 25 years of experience providing some of the world’s most discerning individuals with the best personalized non-invasive acne scar treatment plans. By implementing a customized acne scar treatment plan tailored to you and your acne scars, Dr. Green can significantly diminish their appearance and provide you with a smooth, clear, beautiful complexion that lasts.
How do dermatologists classify the different types of acne scars?
One system for evaluating the severity of acne scars uses grades 1, 2, 3, and 4, which represent macular, mild, moderate, and severe acne scars, respectively. A grade 1 macular acne scar is a flat, smooth scar without texture but with notable post-inflammatory hyperpigmentation. A grade 2 mild acne scar is visible only at a distance of less than 50 cm and can be covered with makeup. A grade 3 moderate acne scar is visible at a distance greater than 50 cm and can’t be covered with makeup. Manually stretching the skin can flatten a grade 3 scar. A grade 4 severe acne scar is evident from a distance and can’t be easily covered. Manually stretching the skin will not flatten a grade 4 scar. No two patients will develop acne scars in the same manner, and most patients have a mixture of multiple grades and types of acne scars. An experienced board-certified dermatologist, such as Dr. Michele Green in NYC, has the expertise to treat acne scars of varying severities, improving overall appearance and achieving smoother, clearer skin texture.

Can you have more than one type of acne scar at once?
Yes—most patients who develop acne scarring have a combination of scar types rather than just one. It is common to see rolling, boxcar, and ice pick scars (also called ice pick scars) alongside overlapping areas of post-inflammatory hyperpigmentation on the same area of skin. Because pitted scars and raised, hypertrophic or keloid scars can coexist, a single treatment approach is rarely enough to address every concern. Dr. Green designs a customized, multimodal treatment plan to address every type of acne scar, rather than forcing a single procedure to treat them all.
How do I identify my acne scar type?
Identifying your acne scar type begins with closely examining the mark’s texture and depth. Depressed or pitted scars—rolling, boxcar, and ice-pick scars—create indentations in the skin’s surface, while raised bumps, including a single raised bump of scar tissue, signal a hypertrophic or keloid scar. Dark spots or discolorations left after a pimple heals are usually post-inflammatory hyperpigmentation rather than true scarring. Because many patients have a mix of scar types that can be difficult to distinguish on their own, a hands-on evaluation with an experienced board-certified dermatologist like Dr. Green is the most reliable way to determine exactly which acne scars you have.
What do the different acne scars look like?
Rolling scars create a wavy, uneven texture with sloping edges, while boxcar scars appear as broader, rectangular depressions with well-defined borders. Ice pick scars are the narrowest and deepest, resembling small puncture marks in the skin. Hypertrophic scars appear as firm, raised bumps that remain within the boundary of the original breakout, whereas keloid scars grow beyond it. Post-inflammatory hyperpigmentation appears as flat, discolored patches rather than a change in skin texture. Each of these scars can also vary in color and severity, which is why Dr. Green performs an in-person skin assessment before recommending an acne scar treatment plan.
What’s the difference between atrophic and hypertrophic scars?
Atrophic scars, including rolling, boxcar, and ice-pick scars, are depressed scars that form when the skin produces too little collagen while healing an acne lesion. Hypertrophic scars, on the other hand, develop when the skin produces excess collagen, creating a firm, raised bump above the surface. Keloid scars are a more extreme form of hypertrophic scarring that can continue to grow beyond the original wound. Understanding whether your acne scarring is atrophic or hypertrophic is essential, since each requires a different treatment approach. Dr. Green evaluates the scar tissue in person to determine the most effective option for your skin.
Are dark spots or red marks actually acne scars (PIH vs PIE)?
Not exactly. Dark spots, known as post-inflammatory hyperpigmentation (PIH), and red or pink marks, known as post-inflammatory erythema, are common after a breakout heals. Still, neither is considered a true acne scar. Both PIH and post-inflammatory erythema occur when the skin’s healing response leaves discoloration rather than a permanent change in skin texture or collagen structure. While these marks can take time to fade, they typically respond well to skincare and in-office treatments, unlike true atrophic or hypertrophic scars, which require more targeted intervention from a board-certified dermatologist like Dr. Green.
What are the hardest acne scars to get rid of?
Ice pick scars are widely considered the most difficult acne scars to treat because of their narrow, deep shape, which makes it hard for lasers and chemical peels to reach the base of the scar tissue. Keloid scars can also be challenging because removal can stimulate new collagen production and lead to recurrence. In more severe cases, Dr. Green may recommend punch excisions or punch grafts to physically remove deep, pitted scars that have not responded to less invasive treatments. With the right combination of approaches, however, even the most stubborn acne scarring can be significantly improved.
Do all acne breakouts result in acne scars?
Not all acne breakouts will result in scarring. Inflammatory acne is the most likely to cause scarring; however, any acne lesion may result in scarring. Nodules and cysts are severe acne lesions marked by significant inflammation. When these breakouts are left untreated, patients will likely develop acne scarring. In addition, picking at and popping pimples can exacerbate acne-related inflammation, significantly increasing the likelihood of scarring. It is essential to start treating acne breakouts with a board-certified dermatologist like Dr. Green as soon as they occur, because preventing an acne scar by treating the breakout is often much more straightforward than reducing the appearance of an acne scar after it has formed.
What is the best skincare routine to complement acne scar treatments?
A proper skincare routine helps maintain and enhance the results of acne scar treatments. Dr. Green’s MGSkinLabs line addresses concerns such as scarring, hyperpigmentation, and fine lines. Retinol and retinoids in the Essential Antioxidant Infusion stimulate collagen production and cell turnover for a smoother complexion, with prescription-strength options available for more severe scarring. Prescription hydroquinone can lighten post-inflammatory hyperpigmentation, while MGSkinLabs’ Vita-C Serum and Skin Brightening Cream offer similar benefits without hydroquinone and are gentle enough for daily use. Finally, broad-spectrum sunscreen, such as MGSkinLabs’ Hydrating SPF 50, is essential for protecting the skin and preventing scars from worsening.
What’s the best treatment for each type of acne scar?
No single treatment works best for acne scars, as the ideal approach depends on the type and depth of scarring. Rolling and boxcar scars often respond well to subcision, dermal fillers, and microneedling, whereas ice-pick scars may require a TCA chemical peel, punch excision, or laser therapy to reach the base of the scar. Hypertrophic and keloid scars typically improve with cortisone injections, while dermabrasion and laser treatments can help refine overall skin texture. For post-inflammatory hyperpigmentation, Dr. Green often recommends a combination of chemical peels, salicylic acid–based exfoliants, gentle at-home exfoliation, and daily high-SPF sunscreen to prevent further discoloration. Because most patients have more than one type of acne scar, Dr. Green builds a personalized plan that combines these tools.
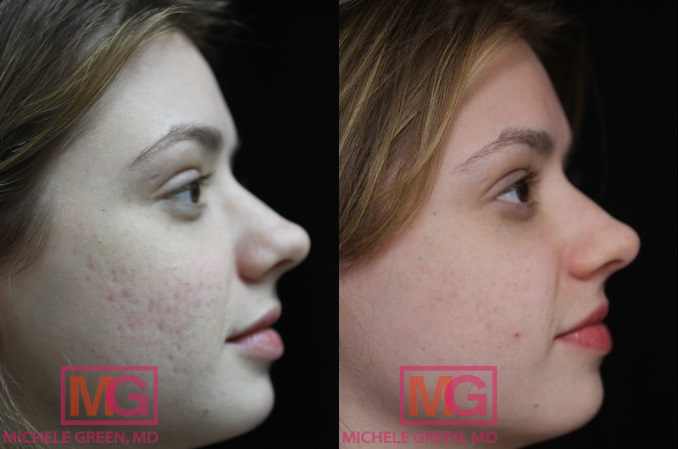
Schedule Your Acne Scar Treatment Consultation with Dr. Michele Green Today
Acne scars—whether atrophic scars such as rolling, boxcar, and ice-pick scars, hypertrophic and keloid scars, or lingering post-inflammatory hyperpigmentation—can be frustrating reminders of past breakouts, but their appearance does not have to be permanent. With today’s combination of subcision, laser treatments, chemical peels, microneedling, and targeted skincare, even the most stubborn acne scarring can improve significantly. The right treatment plan depends on the types of acne scars you have, so a personalized evaluation with Dr. Michele Green in NYC is the best first step toward clearer, smoother skin.
Dr. Michele Green is an internationally renowned, board-certified dermatologist with over 25 years of experience treating acne scars and other skin concerns in her private practice on Manhattan’s Upper East Side. Recognized repeatedly by Castle Connolly, Super Doctors, New York Magazine, and The New York Times as one of New York’s best dermatologists, Dr. Green takes a holistic, less-is-more approach, customizing each acne scar treatment plan to each patient’s unique skin type, tone, and aesthetic goals. To schedule a consultation and begin your journey toward smooth, healthy-looking skin, call Dr. Green’s office at 212-535-3088 or contact us online.
Related Topics
- Find out more about the different types of acne scar treatment available
- Discover how to treat acne scars on the neck, back and body
- Laser treatments for acne scars
- Read about the different types of acne scar removal methods
- Boxcar Acne Scars
- Ice Pick Acne Scars
- Rolling Acne Scars
- Subcision for acne scarring
- Learn more about TCA cross for acne scars


